
CRS & HIPEC for Ovarian Cancer in Kochi
Advanced Surgical Treatment for Selected Ovarian Cancers
Advanced ovarian cancer care with CRS and HIPEC, combining expert cancer surgery with targeted heated chemotherapy for selected patients.
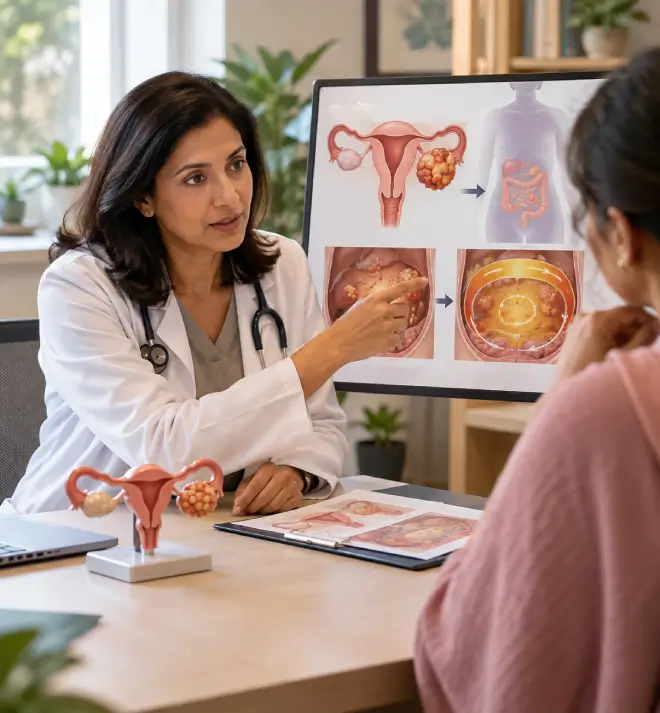
Cytoreductive surgery, or CRS, is an extensive cancer operation performed to remove visible tumour deposits from the abdomen. Depending on where the cancer has spread, surgery may involve removing affected reproductive organs and cancer deposits from different areas of the abdominal cavity. The goal is to achieve the greatest possible removal of visible disease when surgery is considered appropriate.
HIPEC, or hyperthermic intraperitoneal chemotherapy, is a specialised treatment in which heated chemotherapy is circulated inside the abdominal cavity during surgery. It is not required for every woman with ovarian cancer. Whether CRS with HIPEC is appropriate depends on factors such as the extent of disease, response to chemotherapy, overall health and whether complete or near-complete tumour removal can be achieved.
Cytoreductive surgery, commonly shortened to CRS, is a major surgical procedure used in selected patients whose ovarian cancer has spread within the abdominal or peritoneal cavity.
Ovarian cancer can spread across the surfaces inside the abdomen. Tumour deposits may be found around organs and tissues such as the peritoneum, bowel, omentum and other areas of the abdominal cavity.
When surgery is appropriate, the aim of CRS is to remove as much visible cancer as possible.
This is different from a simple operation to remove an ovarian mass. Advanced ovarian cancer surgery can involve several areas of the abdomen, depending on where the disease has spread.
The surgical plan is therefore made after reviewing the patient's scans, pathology, previous treatment and overall condition.
HIPEC stands for Hyperthermic Intraperitoneal Chemotherapy.
It is a form of chemotherapy delivered directly into the abdominal cavity during surgery.
After the visible tumour deposits have been removed as part of cytoreductive surgery, heated chemotherapy is circulated within the abdominal cavity for a specified period. The abdominal cavity is then drained and the surgical procedure is completed.
The idea behind HIPEC is to deliver chemotherapy directly to the surfaces where cancer cells may remain after surgery.
HIPEC is a specialised treatment and is not appropriate for every patient with ovarian cancer. Current evidence and clinical practice continue to evaluate its role in ovarian cancer, with patient selection being an important part of treatment planning.
In selected cases, CRS and HIPEC may be used as part of the same treatment strategy.
CRS focuses on removing visible tumour deposits.
HIPEC focuses on delivering chemotherapy directly into the abdominal cavity after the surgical removal of visible disease.
The two treatments therefore have different roles.
The decision to combine them depends on the patient's disease, response to previous treatment, the possibility of achieving adequate tumour removal and other medical considerations.
It is not a treatment that should be chosen simply because ovarian cancer is advanced. A specialist assessment is needed to determine whether the potential benefits justify the complexity of the procedure.
CRS may be considered when ovarian cancer has spread within the abdomen and the surgical team believes that a meaningful reduction in visible disease can be achieved.
The decision can depend on several factors, including:
Advanced ovarian cancer is not the same in every patient.
Two women can have the same broad diagnosis but have very different patterns of disease within the abdomen. Their treatment plans may therefore be different.
This is why imaging and specialist assessment are important before planning CRS.
Yes, in selected situations.
Chemotherapy is often an important part of ovarian cancer treatment. Depending on the individual case, chemotherapy may be given before surgery to reduce the amount of disease and assess how the cancer responds.
Surgery may then be considered after chemotherapy if the disease appears suitable for cytoreduction.
NCI treatment information includes chemotherapy followed by surgery with HIPEC among treatment approaches for selected ovarian cancer situations.
However, the fact that a patient has received chemotherapy does not automatically mean that CRS and HIPEC will be appropriate.
The response to treatment, current disease distribution and ability to safely remove the visible cancer all need to be considered.
CRS can be a complex operation because ovarian cancer may involve several surfaces and organs within the abdomen.
The exact procedure varies from patient to patient.
Depending on where cancer is found, surgery may involve removal of:
In some advanced ovarian cancers, parts of the bowel or other abdominal structures may be involved.
The purpose of surgery is not simply to remove one tumour. It is to address the overall distribution of visible disease within the abdomen.
The final surgical plan therefore depends on what is found during the assessment and, in some cases, the findings during surgery itself.
The main goal of CRS is to remove as much visible cancer as possible.
For suitable patients, achieving complete cytoreduction, meaning no visible residual disease, is an important surgical objective.
However, this cannot always be achieved safely.
The surgeon has to balance cancer removal with the patient's safety and the function of vital organs.
A good surgical plan therefore considers not only how much cancer can be removed, but also whether the procedure can be performed safely.
This is one of the reasons why advanced ovarian cancer surgery should be planned by a team experienced in complex gynaecologic oncology surgery.
HIPEC is performed during surgery.
After cytoreductive surgery has been completed, a heated chemotherapy solution is introduced into the abdominal cavity.
The solution is circulated for a defined period while the surgical team monitors the procedure. The chemotherapy is then removed and the operation is completed.
The exact chemotherapy drug, concentration, temperature and duration depend on the treatment protocol being followed.
HIPEC is different from standard intravenous chemotherapy because the medication is delivered directly into the abdominal cavity rather than being given only through the bloodstream.
It is a highly specialised procedure that requires appropriate surgical, anaesthesia, oncology and postoperative support.
No.
This is one of the most important things to understand about HIPEC.
Having ovarian cancer does not automatically mean that HIPEC is required or beneficial.
The decision depends on the individual clinical situation.
Factors that may be considered include:
Current evidence continues to examine which ovarian cancer patients are most likely to benefit from HIPEC. NCI notes that the use of HIPEC in ovarian cancer varies by patient selection, treatment approach and clinical setting.
A specialist consultation is therefore important before making a decision about CRS and HIPEC.
Before major ovarian cancer surgery, your doctor will need to understand both the cancer and your overall health.
Depending on your case, this may include:
Your scans are particularly important because they can help the surgical team understand where the cancer is located and whether surgery is likely to achieve the intended goal.
Previous treatment records are also useful, particularly if chemotherapy has already been given.
For advanced ovarian cancer, the distribution of disease inside the abdomen is important.
The surgical team may assess whether tumour is present around structures such as:
The location and extent of these deposits can influence whether complete cytoreduction is realistic.
Sometimes disease that initially appears extensive can still be considered for surgery. In other situations, the pattern of spread may make major surgery unsuitable.
This assessment needs specialist experience rather than relying on a single scan finding.
Standard ovarian cancer surgery may involve removal of the ovaries, fallopian tubes, uterus, omentum and lymph nodes depending on the stage and treatment plan.
CRS is specifically focused on removing visible tumour deposits throughout the abdominal cavity in patients with advanced or disseminated disease.
It can therefore be considerably more extensive than surgery for an ovarian tumour that is confined to the ovary.
The operation is planned according to where the cancer has spread.
This distinction is important because patients searching for "ovarian cancer surgery" may be referring to very different types of operations.
Chemotherapy remains an important part of treatment for many women with ovarian cancer.
Depending on the diagnosis, chemotherapy may be given before or after surgery.
For some patients with advanced disease, chemotherapy before surgery can reduce tumour burden and help determine how the cancer responds to treatment.
After surgery, additional chemotherapy may be recommended depending on the overall treatment plan.
CRS and HIPEC should therefore be viewed as part of a broader ovarian cancer treatment plan rather than as a treatment that replaces all other forms of cancer therapy.
CRS and HIPEC are major treatments, so recovery can take time.
Your recovery depends on the extent of surgery, the organs involved, your general health and whether complications occur.
After surgery, your medical team will monitor:
You may initially need close monitoring in the hospital.
Your return to normal activity will be gradual.
Because CRS can involve extensive abdominal surgery, recovery may take longer than recovery from a routine gynaecological operation.
Your treating team will give you individual instructions about activity, food, wound care, medications and follow-up.
CRS and HIPEC are complex treatments and, like any major cancer surgery, they carry risks.
Potential complications can include:
The risk depends on the extent of disease, the type of surgery performed, your health and other individual factors.
HIPEC can also have treatment-related side effects, which your oncology and surgical team will discuss before treatment.
The purpose of discussing these risks is not to create unnecessary fear. It is to make sure you understand what major surgery involves before deciding whether to proceed.
It is important to be careful with the word cure.
CRS and HIPEC can form part of the treatment strategy for selected ovarian cancer patients, but no responsible doctor can guarantee that a particular procedure will cure an individual patient's cancer.
The outcome depends on factors such as:
Your doctor can discuss the expected goals of treatment after reviewing your individual diagnosis.
Advanced ovarian cancer surgery can involve multiple areas of the abdomen.
The operation may require decisions about how to remove tumour while preserving the function of important organs and maintaining patient safety.
This requires specialised training in gynaecologic oncology and experience with complex cancer surgery.
Dr. Priya Bhati is an Associate Professor in Gynaecologic Oncology at Amrita Hospital, Kochi. She completed her MCh in Gynaecologic Oncology at Christian Medical College, Vellore, and has specialised experience in gynaecologic cancer surgery.
Her official profile specifically lists CRS and HIPEC among her areas of expertise, along with laparoscopic gynaecologic oncology surgery and robotic-assisted gynaecologic cancer surgery.
Advanced ovarian cancer often requires more than one type of cancer specialist.
At Amrita Hospital's Gynaecologic Oncology division in Kochi, ovarian cancer cases are discussed through a multidisciplinary tumour board involving specialists such as medical oncologists, radiation oncologists, radiologists and pathologists when appropriate. The department lists treatment for ovarian cancer, including complete cytoreduction for advanced disease and interval cytoreduction after chemotherapy.
This type of coordinated care can be particularly important when a patient is being considered for complex surgery.
The treatment plan needs to take into account the cancer itself, previous treatment, surgical options and what may be required after surgery.
If you have been advised to consider CRS and HIPEC, it is reasonable to ask your doctor:
Having these questions answered before a major operation can help you understand the proposed treatment.
Consider a specialist gynaecologic oncology consultation if you have:
A second specialist opinion can also be useful if you want your scans, pathology and treatment plan reviewed before proceeding with major surgery.
Being told that your ovarian cancer has spread within the abdomen can be difficult to process. You may hear terms such as cytoreduction, HIPEC, debulking surgery and intraperitoneal chemotherapy without knowing exactly what they mean for your treatment.
The first step is to understand your individual disease.
Dr. Priya Bhati provides specialist gynaecologic oncology care in Kochi and has CRS and HIPEC listed among her areas of expertise. Her training includes an MCh in Gynaecologic Oncology from CMC Vellore, with experience in complex gynaecologic cancer surgery.
If you have been diagnosed with advanced ovarian cancer or have been advised to consider CRS and HIPEC, bring your scan reports, pathology reports and previous treatment records for a specialist consultation.
Your treatment options can then be discussed based on the actual extent of your disease and your overall health.
If CRS or HIPEC has been suggested for you, speak with a gynaecologic oncology specialist before making a decision.
Book a Consultation With Dr. Priya Bhati
1. What is CRS in ovarian cancer?
CRS stands for cytoreductive surgery. It is an extensive cancer operation designed to remove visible tumour deposits from the abdominal cavity in selected patients with advanced ovarian cancer.
2. What does HIPEC stand for?
HIPEC stands for hyperthermic intraperitoneal chemotherapy. It involves circulating heated chemotherapy inside the abdominal cavity during surgery after cytoreductive surgery has been performed.
3. Is HIPEC suitable for every ovarian cancer patient?
No. HIPEC is not suitable for every woman with ovarian cancer. The decision depends on the type and extent of cancer, response to chemotherapy, ability to achieve satisfactory cytoreduction, general health and other clinical factors.
4. Is CRS the same as ovarian cancer surgery?
CRS is a form of ovarian cancer surgery used mainly when cancer has spread within the abdominal cavity. It can be more extensive than surgery for an ovarian tumour confined to the ovary.
5. Can HIPEC be given after chemotherapy?
In selected treatment situations, HIPEC may be considered during surgery after chemotherapy. Whether it is appropriate depends on the patient's disease and response to treatment.
6. Does CRS remove all ovarian cancer?
The aim of cytoreductive surgery is to remove as much visible cancer as possible. In suitable patients, the surgical goal may be complete cytoreduction, meaning no visible residual disease. However, complete removal is not always possible.
7. What organs can be removed during CRS?
The organs and tissues involved depend on where the cancer has spread. Surgery may involve the ovaries, uterus, omentum, peritoneum and, in some advanced cases, portions of other affected abdominal structures.
8. Is CRS and HIPEC a major surgery?
Yes. CRS and HIPEC are complex treatments and can involve extensive abdominal surgery. Patients need careful assessment before treatment and close monitoring during recovery.
9. How long does recovery take after CRS and HIPEC?
Recovery varies significantly depending on the extent of surgery and the patient's overall health. Because CRS can involve multiple areas of the abdomen, recovery can take considerably longer than after routine gynaecological surgery.
10. What are the risks of CRS and HIPEC?
Potential risks include bleeding, infection, blood clots, bowel complications, fluid and electrolyte problems, wound complications and other complications associated with major abdominal surgery. HIPEC can also have chemotherapy-related side effects.
11. Will I need chemotherapy after CRS and HIPEC?
Possibly. Additional chemotherapy may be recommended depending on the cancer type, surgical findings, pathology and the overall treatment plan. Your oncology team will advise you based on your individual case.
12. Can recurrent ovarian cancer be treated with CRS and HIPEC?
In selected cases, surgery and HIPEC may be considered for recurrent ovarian cancer. However, recurrent disease is highly individual, so the treatment decision requires detailed review of previous treatment and current disease.
13. What tests are needed before CRS and HIPEC?
Your doctor may review CT or other imaging, pathology reports, blood tests, tumour markers, previous chemotherapy records and your general health before deciding whether CRS and HIPEC should be considered.
14. Is HIPEC the same as regular chemotherapy?
No. Standard chemotherapy is commonly administered through the bloodstream, while HIPEC involves delivering heated chemotherapy directly into the abdominal cavity during surgery.
15. Does HIPEC guarantee that ovarian cancer will not return?
No. No cancer treatment can guarantee that ovarian cancer will not return. The risk of recurrence depends on several factors, including the type and extent of cancer, treatment response and completeness of tumour removal.
16. Can I get a second opinion before CRS and HIPEC?
Yes. A second opinion can help you understand whether major surgery and HIPEC are appropriate for your particular diagnosis. Take your pathology, scans and previous treatment records to the consultation.
17. Who performs CRS and HIPEC for ovarian cancer in Kochi?
Dr. Priya Bhati is a Gynaecologic Oncology specialist at Amrita Hospital, Kochi, and her official profile lists CRS and HIPEC among her areas of expertise.
18. Where can I consult for CRS and HIPEC for ovarian cancer in Kochi?
You can consult Dr. Priya Bhati in Kochi for specialist assessment of ovarian cancer and discussion of CRS and HIPEC when clinically appropriate. Amrita Hospital's Gynaecologic Oncology division lists CRS and HIPEC among its specialised services.

MBBS, M. Ch. (Gynaecologic Oncology), MD (Obs & Gynae)
Senior Consultant - Gynae Oncologist and Robotic Surgeon, Department of Gynecologic Oncology, Amrita Institute of Medical Sciences, Kochi, Kerala
Dr. Priya Bhati is a Senior Consultant Gynae Oncologist and Robotic Surgeon at Amrita Institute of Medical Sciences, Kochi. She specialises in the treatment of gynaecological cancers and complex gynaecological conditions, with expertise in cancer surgery, robotic-assisted surgery and laparoscopic surgery. With years of experience at leading institutions such as CMC Vellore and PGIMER Chandigarh, she brings extensive surgical experience along with a caring and patient-focused approach.
Dr. Priya has completed her M.B.B.S. from Kasturba Medical College, Mangalore, M.D. in Obstetrics & Gynecology from Goa Medical College, and M.Ch. in Gynaecologic Oncology from Christian Medical College, Vellore. She treats women with different types of gynaecological cancers and also performs complex benign gynaecological surgeries and advanced procedures such as CRS and HIPEC.
She believes that every patient deserves to understand her condition and treatment clearly. Along with treating gynaecological cancers, Dr. Priya also focuses on prevention and early detection, including HPV vaccination and preventive gynaecologic care. Her goal is to provide personalised treatment while making patients and their families feel informed, comfortable and supported throughout their care.
I was very scared when I came to know about my cancer. Dr. Priya Bhati explained everything clearly and told me what we should do next. I am really thankful for her support.
Dr. Bhati is very patient and listens to all your doubts. She explained my reports in simple words and did not make me feel rushed. I felt much better after talking to her.
We met Dr. Priya Bhati for my mother’s treatment. She explained the surgery properly and answered all our questions. We felt that she really understood our concerns.
I was worried about having surgery, but Dr. Bhati explained the procedure and what to expect. She was very calm and supportive. I am happy that we consulted her.
Dr. Bhati gave us enough time during the consultation and explained the treatment options clearly. She also listened to what we wanted to know. Very good doctor and a very positive experience.
After my diagnosis, I was confused about what to do next. Dr. Bhati went through my reports and explained everything step by step. Her guidance gave me confidence to start my treatment.